
Three Lines Across One Body
Jurisdiction follows function.
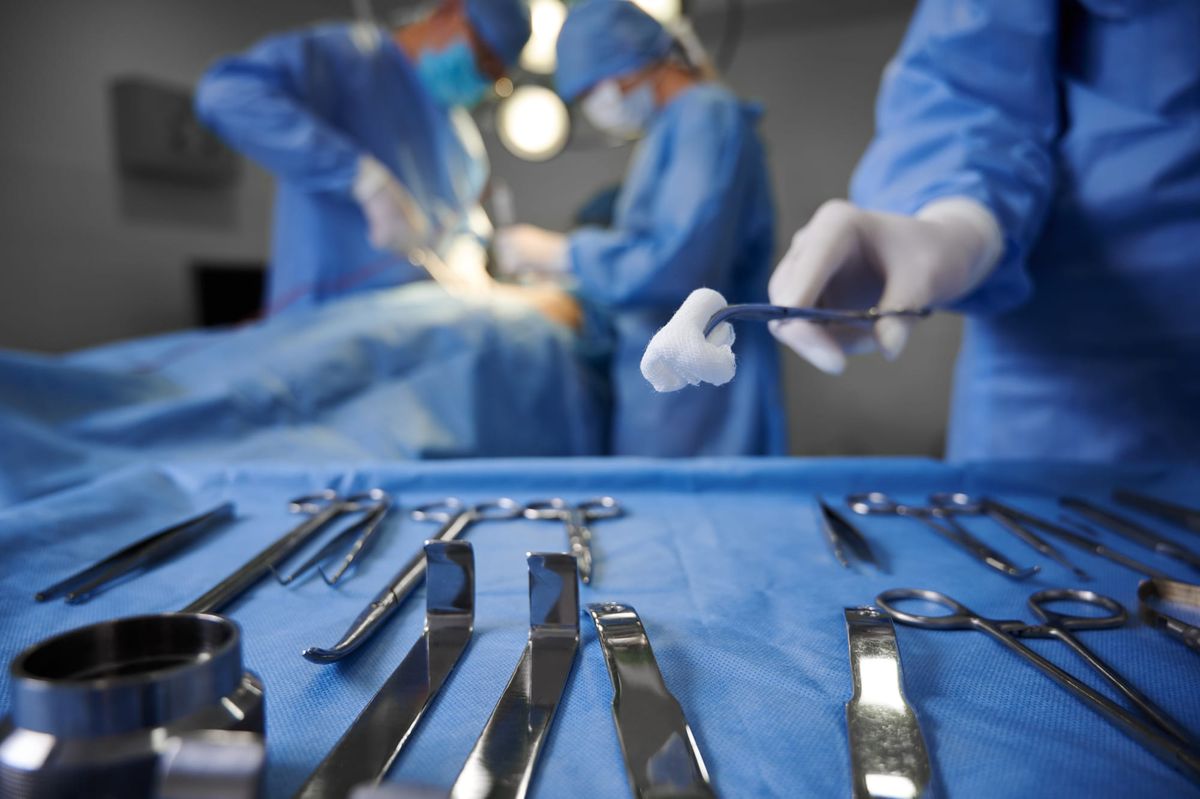
The surgeon says stop.
Seven people obey.
The patient has authorized a bounded procedure and is now under anesthesia. Her signed form, marked with questions and limits in her own hand, remains inside the room.
A navigation display hangs above the operative field.
An anesthesia monitor carries another account of the patient's body.
The circulating nurse has the count and a separate stop line.
A remote device engineer occupies a small rectangle on a screen.
Outside the room, the hospital has assembled staff, supplies, power, records, money, and time around a schedule that assumed the operation would proceed as planned.
- The surgeon says stop.
- Hands stop.
- The device pauses.
- The nurse marks the time.
- The device pauses.
- Hands stop.
This is what authority is for.
A body is open. Knowledge is uneven. Seven people cannot renegotiate the constitution of the operating room before every movement. Someone has to coordinate hands, instruments, medication, information, and time.
Equal operational votes would distribute danger while calling the delay respect.
The surgeon has a real last word here.
Then the engineer speaks.
The Machine.
The navigation system has marked a boundary because one input no longer fits the conditions under which its guidance was validated.
The engineer can explain the software version, the signal, the architecture, and the warning. The engineer may understand the instrument better than anyone else in the room. Everyone should listen.
The engineer still cannot authorize an incision.
That distinction is small enough to disappear under pressure.
Expertise gives some claims greater weight.
Sometimes dramatically greater weight.
A trained engineer should receive more authority over the technical behavior of the navigation system than a person encountering it for the first time.
The surgeon likewise has unusual contact with the operative field.
The anesthesiologist has unusual contact with another changing relation inside the patient’s body.
The nurse has responsibilities the surgeon cannot simply absorb.
And the patient’s prior instructions remain active even though she cannot speak.
Knowing more about one part of the field does not create title over everything that part touches.
- The engineer knows the instrument.
- The surgeon knows the operation.
- Neither knowledge includes the patient’s whole life.
Follow the Function.
Status is a poor map of jurisdiction.
So is ownership.
So is expertise.
So is urgency.
Each can support real authority. Each can also be promoted beyond the work that justified it.
A harder question begins with function:
What work justifies this power?
The surgeon’s operational authority exists to coordinate the patient’s authorized procedure toward its protective end.
That function can require fast commands. It can require access to the patient’s body. It can require people in the room to follow one lead.
It does not grant authority over the patient’s employment, property, religion, relationships, politics, or every future medical decision.
The device engineer’s expertise can interrupt the procedure. It cannot become surgical command.
The payer may determine whether a financial claim satisfies a coverage rule. That does not make the payer the authority on what the surgeon physically sees.
Public regulators can impose rules capable of closing the room entirely. They do not thereby become the people performing the operation.
A jurisdictional warrant connects a legitimate function to the bounded power required to carry it. The boundary matters as much as the grant.
- “Safety” is too large if every human activity can be absorbed beneath it.
- “Efficiency” is too large.
- “Innovation” is too large.
- “Public interest” can become nearly infinite.
A workable function has to identify what is being protected, which powers are required, what remains outside the grant, and where correction can arrive.
Then the operation stops following the plan.
The Form Did Not Predict This.
The operative field reveals an unexpected condition.
Delay now creates a serious immediate danger.
The patient cannot answer. Her prior authorization did not describe this exact event.
The navigation system recommends extending the procedure.
The surgeon believes some extension is necessary.
A simple theory of consent now fails.
- The patient did not authorize this precise act.
- She also did not authorize the team to abandon her to an unforeseen danger because nobody predicted the correct sentence for a form.
A constitution that forbids every action beyond exact prior description would make protection impossible whenever reality produces something new.
The surgeon has to act.
That does not make the emergency a blank check. The danger has to be present, specific, and supported by more than the surgeon’s declaration.
The anesthesiologist keeps a separate stop condition.
The nurse keeps hers.
The navigation system displays its uncertainty.
The engineer’s account remains attached to the record.
The team can address the immediate danger.
This new opening does not carry unrelated treatment through with it.
It does not authorize research enrollment.
It does not transfer the patient’s property.
It does not turn the surgeon into the official interpreter of what the patient would want in every adjacent decision.
The surgeon chooses an extension narrower than the navigation system recommends. The nurse marks the changed boundary. The anesthesiologist confirms that the separate stop condition has not been reached.
The action proceeds.
This is authority working.
This is also a wound.
Valid Authority Can Still Hurt.
The patient will now wake inside a decision she did not make.
The extension may add recovery time, risk, cost, pain, time away from work, or a changed relation to her own body.
The team may have acted reasonably. The action may have been necessary.
Later review can judge whether the emergency warrant was satisfied.
None of that gives the patient the missing choice back.
A valid decision does not become innocent because it was valid.
That is why bounded authority needs a record strong enough to let the next case change.
- What happened?
- What evidence activated the exception?
- Which powers expanded?
- How far?
- Who objected?
- What did the model recommend?
- What did the surgeon actually do?
- When did ordinary authority return?
Those kinds of questions preserve the difference between a protective extension and a permanent enlargement of jurisdiction.
The danger begins when one legitimate function starts swallowing the functions around it.
Function Capture
- The payer has a legitimate function.
- Finite pooled resources need records, rules, and stewardship.
- Function capture begins when the payer’s categories become the medical object because the hospital cannot schedule, staff, or reimburse anything outside them.
- Finite pooled resources need records, rules, and stewardship.
- The safety office has a legitimate function.
- It may need to stop a dangerous action.
- Capture begins when the same office defines the danger, owns the evidence, selects the reviewers, controls the duration, and decides when its own stopping power ends.
- It may need to stop a dangerous action.
- A technology provider has a legitimate function.
- It can maintain systems, preserve compatibility, patch failures, and support continuity.
- Capture begins when records, training, workflows, procurement, and operation cannot survive leaving its interface.
- It can maintain systems, preserve compatibility, patch failures, and support continuity.
None of these institutions needs to announce a claim to rule. The surrounding field becomes practically subordinate to the function they already carry.
This is where private policy, professional custom, or technical default can become constitutional.
Not every recurring decision deserves that treatment. A small voluntary project needs room to build. A laboratory should not require a constitutional convention before changing an internal workflow.
The threshold rises when a recurring power becomes load-bearing for bodies, rights, property, public money, infrastructure, or the ability of other institutions to act.
At that point, “this is how our system works” is no longer enough.
The power needs a warrant. A boundary. Outside correction.
A way to hand off the function.
A way to lose it.
Three Lines.
After the operation, the image returns to the wall.
- The surgeon marks the point where immediate danger required the extension.
- The patient marks the point where the team’s protection crossed a value her earlier instructions had failed to carry.
- An independent reviewer marks the point where the navigation evidence and the emergency rule should have changed the act.
All three lines concern the same event.
None contains it.
- The surgeon carried one function.
- The patient carried another authority through the body and the prior answer.
- The reviewer carries another route by which the first two can change what happens next time.
No one line becomes the whole operation because it is the line drawn by the person with the highest status, the best model, the strongest credential, or the greatest power to act.
Jurisdiction follows function.




Comments ()